Scarring alopecia

Scarring alopecia, also called cicatricial alopecia, refers to a group of hair loss disorders in which inflammation permanently damages the hair follicle and replaces it with scar tissue. Unlike more common forms of hair loss, scarring alopecia can lead to irreversible hair loss if not recognized and treated early.
These conditions are often misunderstood or mistaken for regular hair loss, dandruff or breakage. However, symptoms such as scalp burning, itching, tenderness, bumps, pustules or rapid thinning may signal active inflammatory disease that requires medical treatment.
Modern therapies can often slow or stop progression, reduce inflammation, improve symptoms and help preserve remaining hair.
Common types of scarring alopecia
Lichen Planopilaris (LPP) and Fibrosing Alopecia in a Pattern Distribution (FAPD)
Frontal Fibrosing Alopecia (FFA)
Central Centrifugal Cicatricial Alopecia (CCCA)
folliculitis decalvans
Dissecting cellulitis of the scalp
Discoid Lupus Erythematosus (DLE)
Acne Keloidalis Nuchae (AKN)
What causes scarring alopecia?
The exact cause depends on the specific subtype, but most forms involve an abnormal inflammatory response targeting the hair follicle stem cells located in the bulge region of the follicle. Once these stem cells are destroyed, the follicle loses its ability to regenerate hair.
Researchers believe scarring alopecia develops through a combination of:
immune system dysregulation
genetic susceptibility
environmental triggers
alterations in the scalp microbiome
mechanical or chemical injury in some cases
Different types involve different inflammatory pathways.
Evidence-based understanding of common causes
Autoimmune and immune-mediated inflammation
Several forms of scarring alopecia are believed to be autoimmune or immune-mediated disorders in which the immune system mistakenly attacks the hair follicle.
This is especially true for:
Lichen Planopilaris (LPP)
Frontal Fibrosing Alopecia (FFA)
Discoid Lupus Erythematosus (DLE)
Findings include inflammatory lymphocytes targeting the follicular bulge region, where stem cells reside.
Pathways implicated include:
interferon signaling
Peroxisome proliferator-activated receptor gamma (PPAR-gamma) pathways
fibrosis pathways
Janus kinase–signal transducer and activator of transcription (JAK-STAT) signaling
loss of immune privilege around the follicle
Genetic predisposition
Familial clustering in frontal fibrosing alopecia and central centrifugal cicatricial alopecia
Higher prevalence of central centrifugal cicatricial alopecia among women of African descent
Immune-related genetic associations in Lichen Planopilaris
Genetics increases susceptibility but is not sufficient alone to cause disease.
Hormonal factors
Frontal fibrosing alopecia most commonly affects postmenopausal women
Androgen-related pathways may contribute
Some patients respond to finasteride or dutasteride
Hair care practices and mechanical stress
These do not directly cause scarring alopecia but may contribute in susceptible individuals.
Associated factors include:
chronic traction from tight hairstyles
excessive heat styling
chemical relaxers
repeated scalp trauma
friction from helmets or collars
close shaving in some inflammatory conditions
Bacterial and microbial factors
Relevant in neutrophilic scarring alopecias such as:
folliculitis decalvans
dissecting cellulitis
Findings:
Staphylococcus aureus is commonly associated with folliculitis decalvans
disease reflects both infection and immune dysregulation
Symptoms of scarring alopecia
progressive hair thinning or bald patches
scalp burning or pain
itching or tenderness
flaking or scale
redness
pustules or drainage
tufted hairs
loss of follicular openings
shiny scarred scalp
How scarring alopecia is diagnosed
Clinical examination
assessment of pattern of hair loss
evaluation for inflammation, scale and scarring
Trichoscopy
perifollicular scale
erythema
hair tufting
follicular dropout
white scarring areas
Scalp biopsy
essential for confirming diagnosis
helps define inflammatory subtype
Laboratory Evaluation
used when autoimmune disease is suspected
Treatment goals
halt disease progression
reduce inflammation
relieve symptoms
prevent permanent follicular destruction
preserve hair density
Early treatment is critical because destroyed follicles cannot regenerate.
Evidence-based treatments for scarring alopecia
Treatment is individualized and often combination-based.
Topical Treatments
topical corticosteroids: reduce inflammation in active disease
topical calcineurin inhibitors (tacrolimus, pimecrolimus): steroid-sparing anti-inflammatory agents
topical minoxidil: supports growth from remaining viable follicles
Used in:
Lichen Planopilaris (LPP)
Frontal Fibrosing Alopecia (FFA)
Central Centrifugal Cicatricial Alopecia (CCCA)
Discoid Lupus Erythematosus (DLE)
Acne Keloidalis Nuchae (AKN)
Injectable Treatments
intralesional corticosteroid injections: suppress active inflammation locally
Used in:
Lichen Planopilaris (LPP)
Frontal Fibrosing Alopecia (FFA)
Central Centrifugal Cicatricial Alopecia (CCCA)
Discoid Lupus Erythematosus (DLE)
Acne Keloidalis Nuchae (AKN)
Oral and systemic treatments
tetracycline antibiotics (doxycycline, minocycline): anti-inflammatory and antimicrobial effects
hydroxychloroquine: immune modulation in lymphocytic scarring alopecias
oral corticosteroids: short-term control of aggressive inflammation
immunomodulators (methotrexate, mycophenolate mofetil, cyclosporine, azathioprine): for refractory disease
5-alpha reductase inhibitors (finasteride, dutasteride): particularly in frontal fibrosing alopecia and fibrosing alopecia in a pattern distribution
Isotretinoin: useful in neutrophilic scarring alopecias
Low-dose oral naltrexone
Low-dose oral naltrexone is an emerging immunomodulatory therapy used in inflammatory scarring alopecias.
Used in:
Lichen Planopilaris (LPP)
Frontal Fibrosing Alopecia (FFA)
Fibrosing Alopecia in a Pattern Distribution (FAPD)
Central Centrifugal Cicatricial Alopecia (CCCA)
Potential benefits:
reduction in scalp burning, itching and tenderness
decreased perifollicular inflammation
improved symptom control and quality of life
possible adjunctive disease stabilization
Biologic and targeted therapies
Janus kinase (JAK) inhibitors
Tumor necrosis factor-alpha inhibitors
Interleukin-17 and interleukin-23 targeted therapies
Low-dose oral naltrexone as adjunct immunomodulatory therapy
Lichen Planopilaris (LPP) and Fibrosing Alopecia in a Pattern Distribution (FAPD)
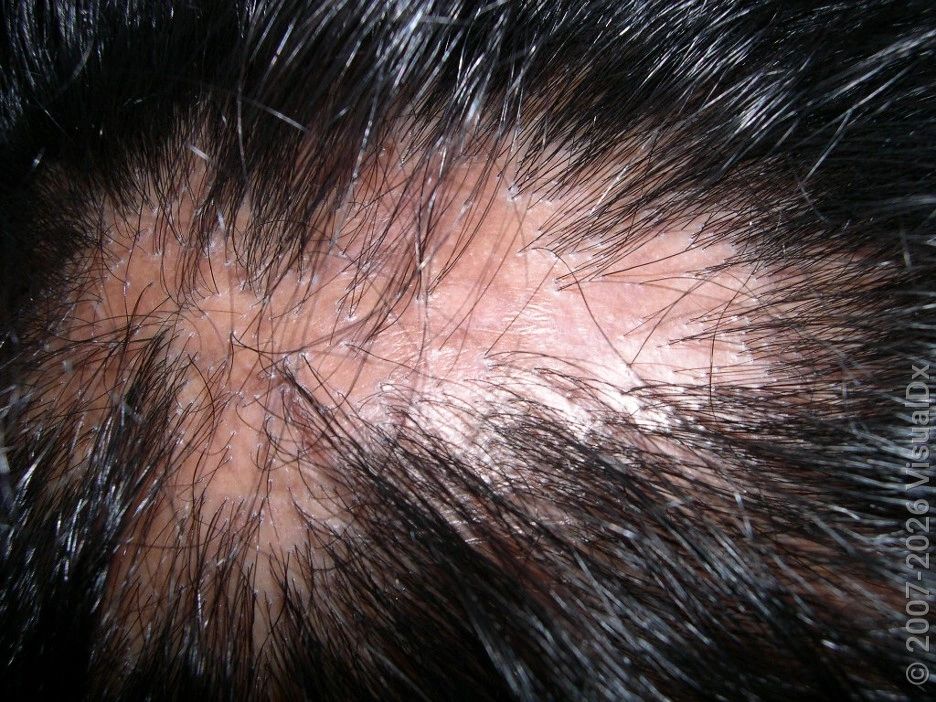
LPP is an inflammatory scarring alopecia in which the immune system targets hair follicles, leading to permanent follicle destruction if not controlled early. FAPD is considered an overlapping condition that combines features of LPP with androgenetic hair loss, often requiring a combination treatment approach.
Treatment focuses on stopping active inflammation to prevent further irreversible hair loss. Topical corticosteroids are commonly used to reduce surface inflammation and symptoms such as itching or burning. Intralesional corticosteroid injections are often used along areas of active disease to directly suppress follicular inflammation.
Oral anti-inflammatory therapies are frequently required for more widespread or progressive disease. These include doxycycline for its anti-inflammatory effects and hydroxychloroquine for immune modulation. In more active cases, systemic immunomodulators such as methotrexate or mycophenolate mofetil may be used, and short courses of oral corticosteroids may be considered for rapid disease control.
Low-dose oral naltrexone (LDN) is increasingly used as an adjunctive off-label therapy in inflammatory scarring alopecias. It is thought to help regulate immune dysregulation and reduce inflammatory signaling. Patients may report improvement in scalp burning, tenderness, and overall inflammatory symptoms when LDN is added to a standard regimen.
Supportive care includes gentle hair practices, avoidance of traction or chemical irritation, and symptom-directed therapies for scalp discomfort.
Frontal Fibrosing Alopecia
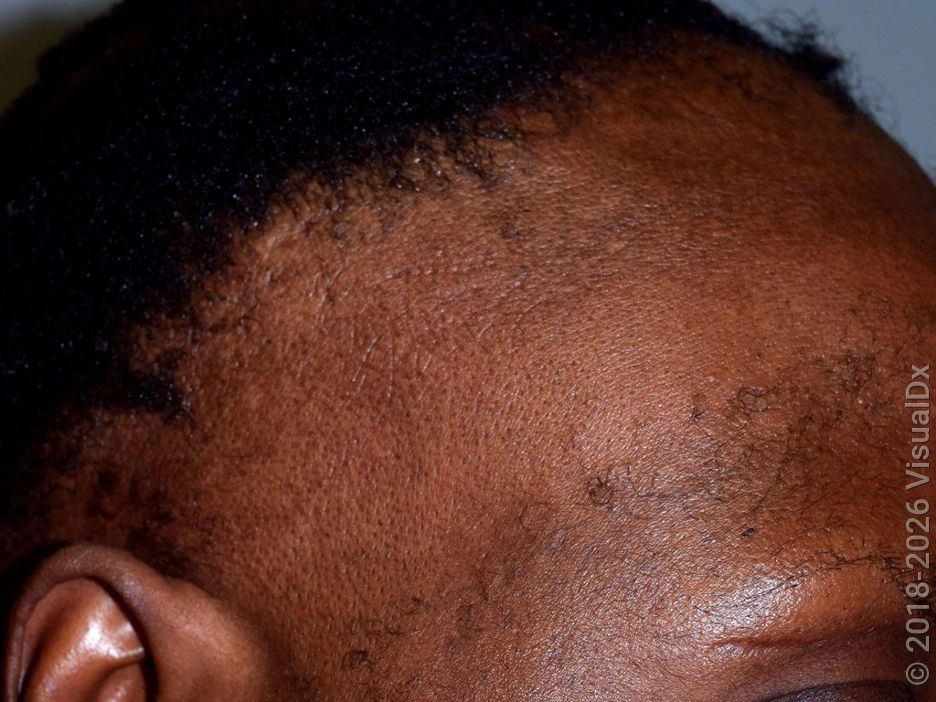
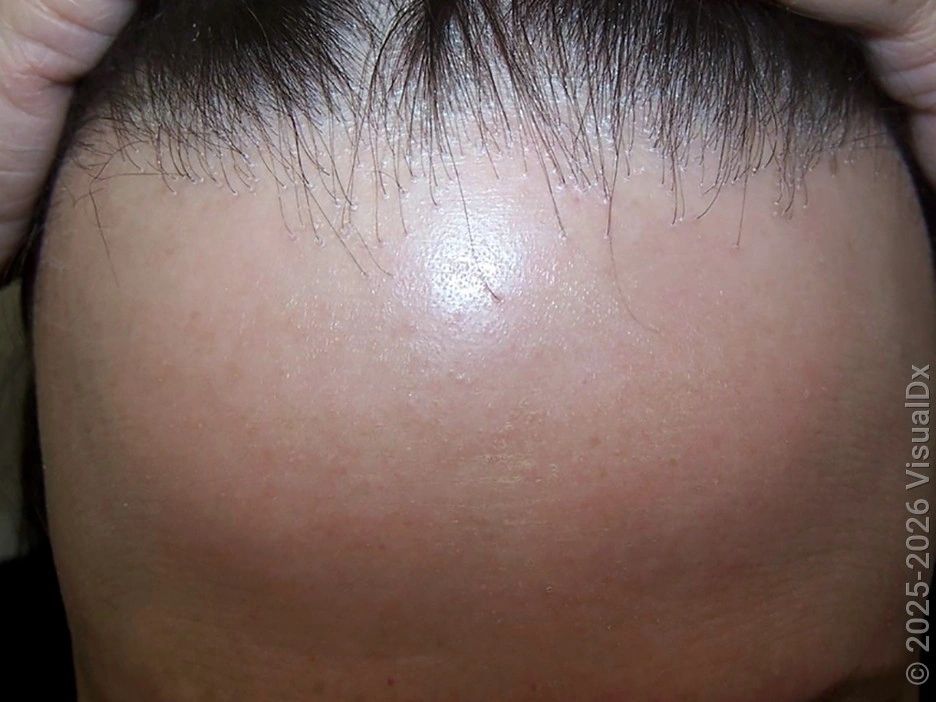
Frontal Fibrosing Alopecia (FFA) is a progressive scarring alopecia characterized by recession of the frontal and temporal hairline and often eyebrow thinning. It is most commonly seen in postmenopausal women but can occur in other populations.
Early symptoms may include scalp itching, burning or tenderness along the hairline. As the disease progresses, follicles are permanently destroyed and replaced with smooth, pale skin.
Treatment is focused on halting progression rather than regrowing scarred follicles. Topical corticosteroids and topical calcineurin inhibitors are used to reduce inflammation. Intralesional corticosteroid injections along the hairline and eyebrows are commonly used to control active disease.
Oral therapies such as doxycycline and hydroxychloroquine are frequently used to reduce inflammation and stabilize disease activity. In more aggressive cases, systemic immunomodulators such as methotrexate or mycophenolate mofetil may be considered. Short courses of oral corticosteroids may be used in rapidly progressive disease.
5-alpha reductase inhibitors such as finasteride or dutasteride may be considered in select patients, particularly when there is overlap with androgenetic alopecia.
Low-dose oral naltrexone may be used as an adjunct to help modulate immune activity and reduce inflammatory symptoms, particularly scalp discomfort.
Hair transplantation is only considered once the disease has been inactive for a prolonged period, as active inflammation can destroy transplanted grafts.
Central Centrifugal Cicatricial Alopecia (CCCA)

CCCA is a progressive scarring alopecia that begins at the crown of the scalp and spreads outward symmetrically. It is most commonly seen in women of African descent but can affect all populations.
Patients may notice gradual thinning at the crown, increased shedding, breakage or scalp tenderness. Over time, the scalp may become smooth and shiny due to permanent follicle loss.
Treatment focuses on stopping inflammation and preserving remaining follicles. Topical corticosteroids are used to reduce inflammation, often combined with topical calcineurin inhibitors for maintenance therapy. Intralesional corticosteroid injections are frequently used in active areas.
Oral anti-inflammatory agents such as doxycycline are commonly used for long-term control. Hydroxychloroquine or other systemic immunomodulators may be required in more severe cases.
Avoidance of traction hairstyles, heat and chemical trauma is an essential part of management.
Low-dose oral naltrexone may be used as an adjunctive therapy in selected patients to help reduce inflammatory signaling and may be particularly helpful for scalp tenderness or burning.
Folliculitis decalvans
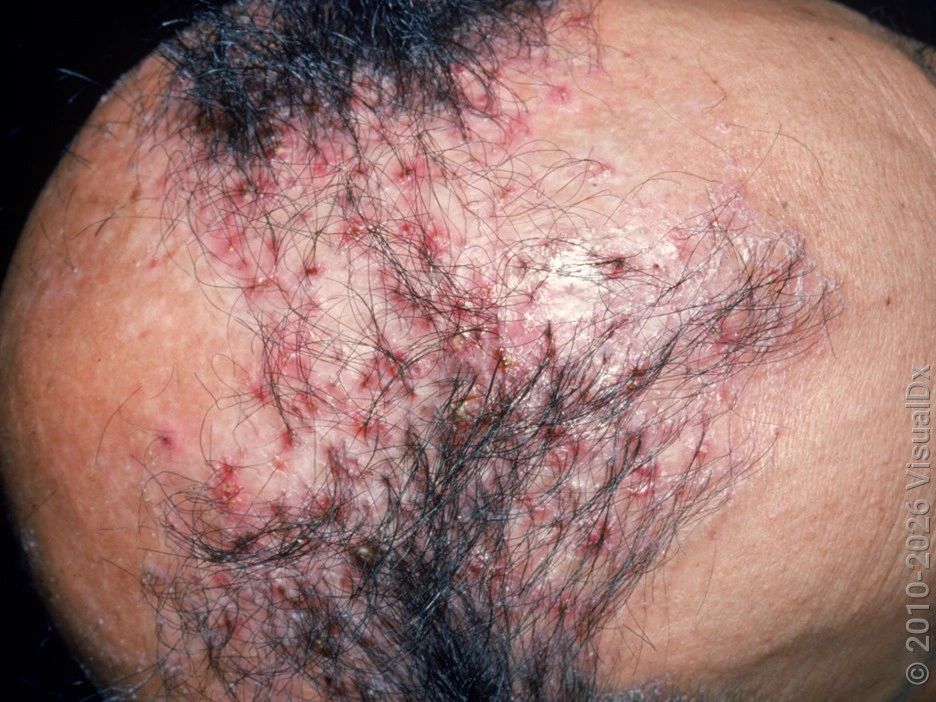
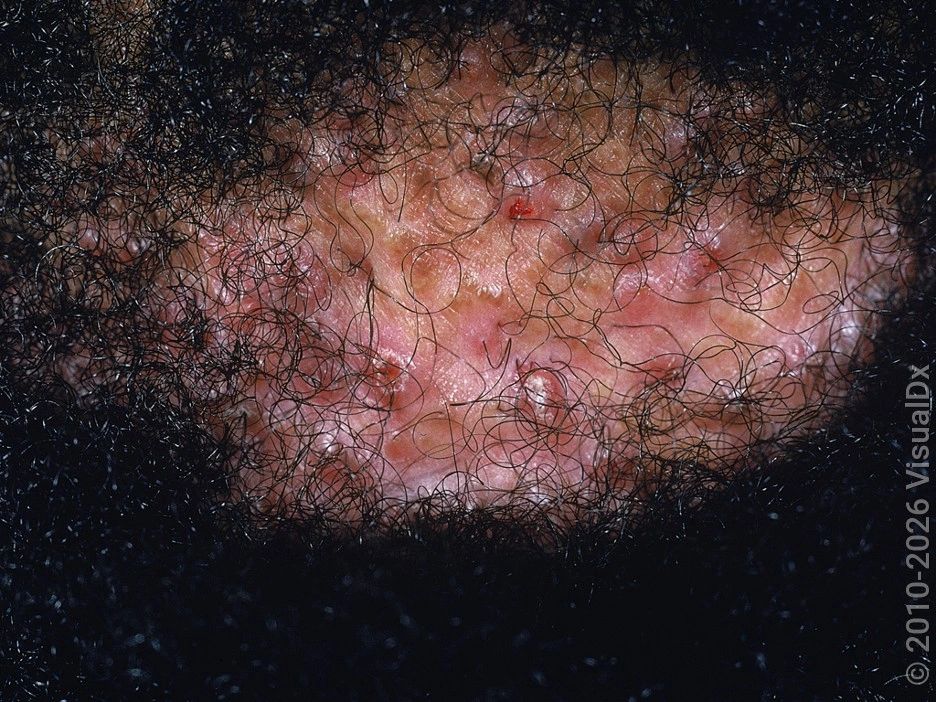
Folliculitis decalvans is a chronic inflammatory condition driven by abnormal immune response to bacteria on the scalp, most commonly Staphylococcus aureus, leading to recurrent infection and scarring hair loss.
Patients may develop painful pustules, crusting, redness and sometimes drainage. A hallmark finding can be “tufted” hairs, where multiple hairs emerge from a single follicular opening.
Treatment requires both antimicrobial and anti-inflammatory strategies. Oral antibiotics such as tetracyclines are commonly used for their dual antimicrobial and anti-inflammatory effects. Combination antibiotic regimens may be used in more severe cases.
Topical antiseptic washes and medicated shampoos are often used for maintenance. Intralesional corticosteroid injections can help control active inflammation.
Isotretinoin may be considered in refractory cases. Biologic therapies may be used in severe, treatment-resistant disease.
Low-dose oral naltrexone may be considered in select patients as an adjunct for persistent inflammatory symptoms, though it is not a primary therapy.
Dissecting cellulitis of the scalp
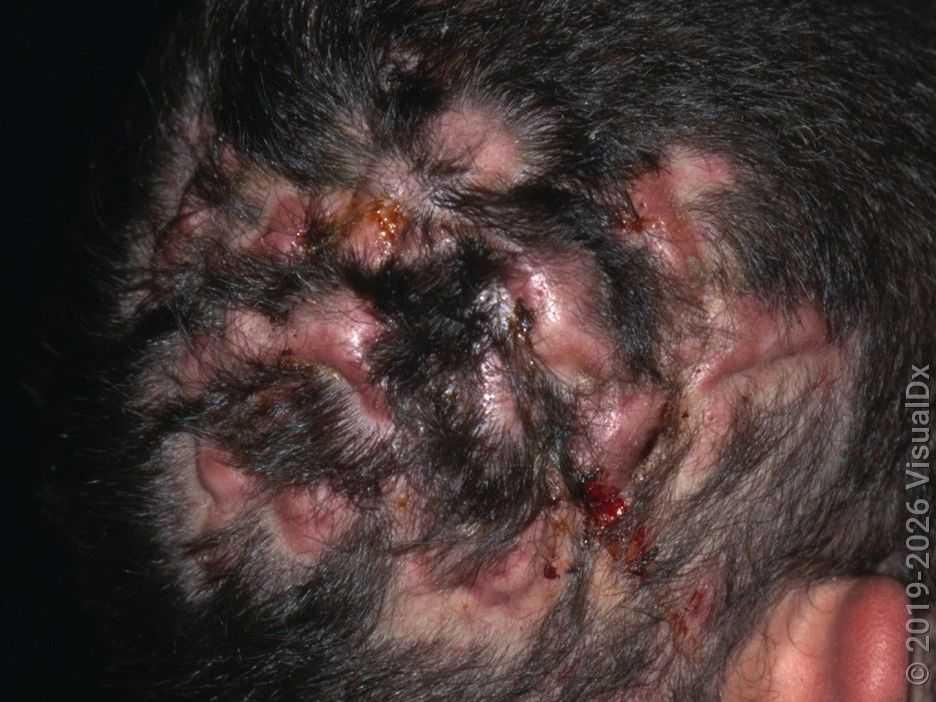
Dissecting cellulitis of the scalp is a chronic inflammatory condition characterized by painful nodules, abscesses and sinus tracts that can lead to scarring hair loss.
Treatment is typically multi-modal and long-term. Oral antibiotics are often used initially to reduce inflammation and secondary infection. Isotretinoin is one of the most effective medical therapies for long-term disease control.
Intralesional corticosteroid injections can reduce localized inflammation. In severe cases, biologic therapies targeting inflammatory pathways may be required. Surgical intervention may be necessary for persistent sinus tracts or advanced scarring disease.
Low-dose oral naltrexone may be used as an adjunctive therapy in select cases for immune modulation and symptom control.
Discoid Lupus Erythematosus
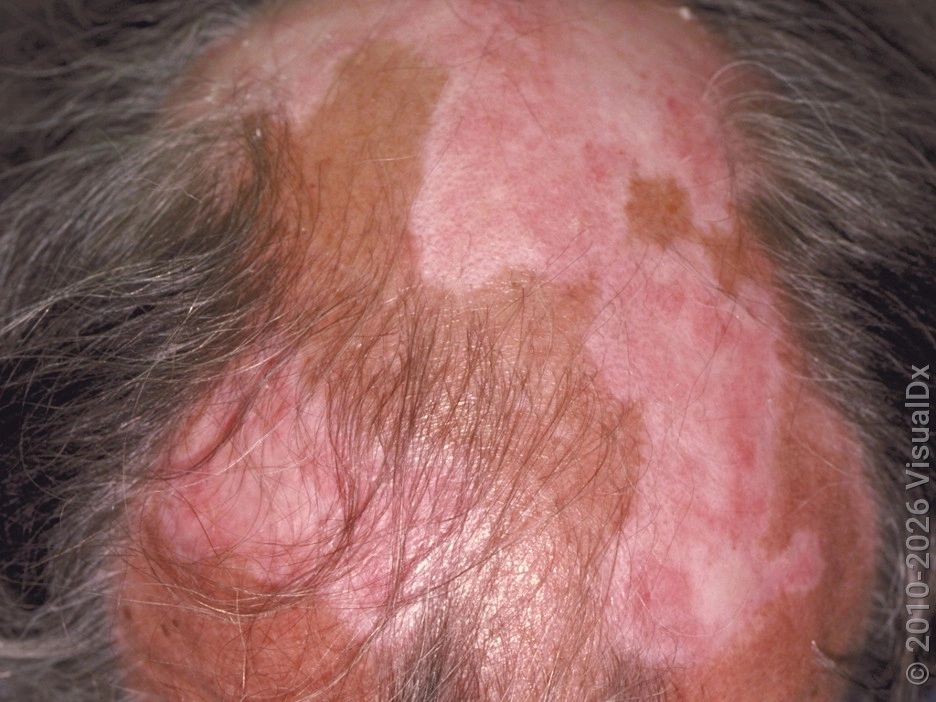
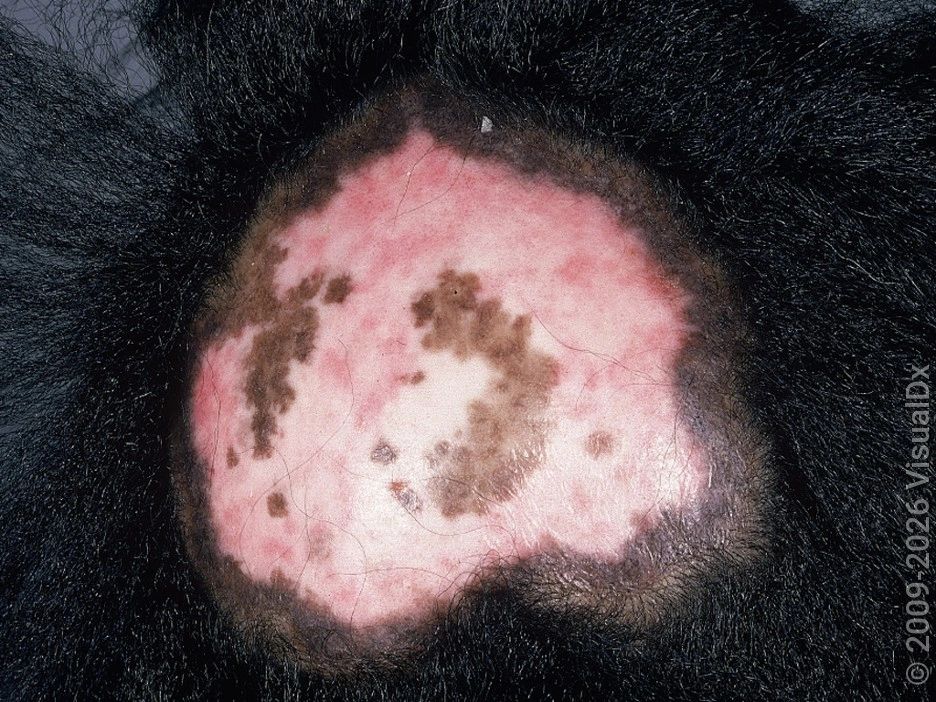
Discoid Lupus Erythematosus (DLE) is an autoimmune condition in which the immune system attacks the skin and scalp, leading to chronic inflammation and scarring hair loss.
Treatment focuses on immune control and prevention of progression. High-potency topical corticosteroids are commonly used for active lesions, along with intralesional corticosteroid injections for thicker plaques. Topical calcineurin inhibitors may be used for maintenance therapy.
Systemic treatment often includes hydroxychloroquine, which is a cornerstone therapy. More severe cases may require additional immunosuppressive agents.
Sun protection is essential, as ultraviolet exposure can worsen disease activity.
Low-dose oral naltrexone may be considered in select patients as an adjunctive therapy, although evidence is more limited compared to standard antimalarial therapy.
Acne Keloidalis Nuchae (AKN)
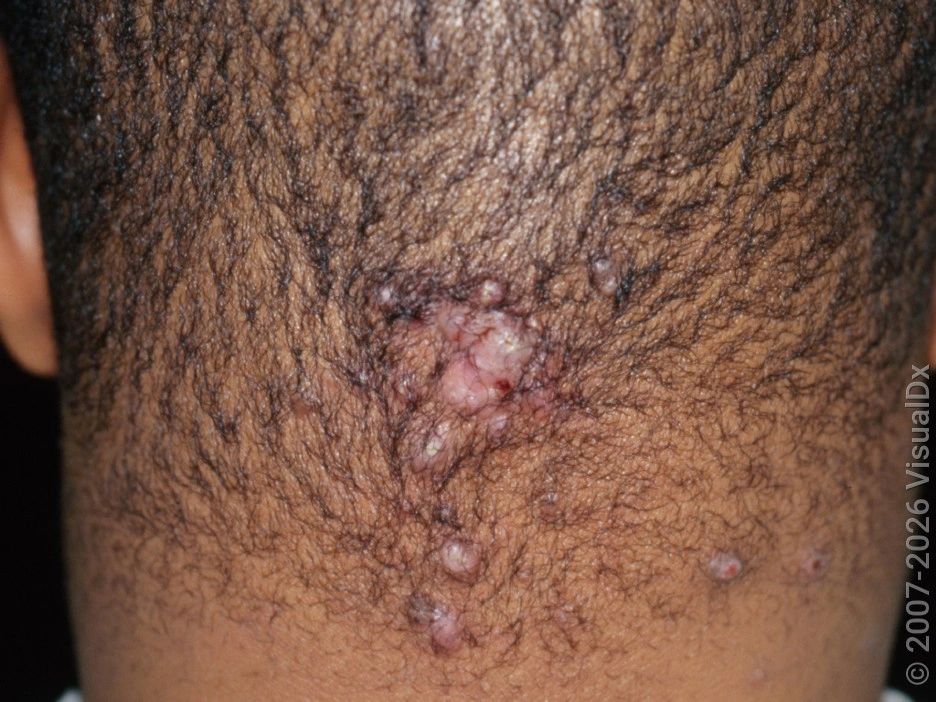
Acne keloidalis nuchae is a chronic inflammatory condition affecting hair follicles at the back of the neck and lower scalp. It can cause bumps, scar-like plaques and permanent hair loss. Early diagnosis helps guide treatment and prevent progression.
Management depends on the severity and may include changes to grooming practices and dermatologist-directed treatment. Read the American Academy of Dermatology explanation.
Can hair regrow?
Hair regrowth depends on follicular viability.
Early disease may partially improve with treatment.
Fully scarred areas generally cannot regrow hair.
The importance of early diagnosis
to preserve existing hair
to reduce irreversible scarring
to improve symptoms and quality of life
To prevent progression of permanent hair loss
Patients with scalp symptoms or unexplained hair loss should seek evaluation by a dermatologist experienced in hair disorders and scalp disease.
Talk with Dr. Agbai
A medical evaluation with NorCal Hair Doctor™ helps determine which treatments fit your diagnosis. Some treatments discussed above are off-label or emerging and require an individual assessment of evidence, benefits and risks.
Request a consultation or call (916) 571-5200.